
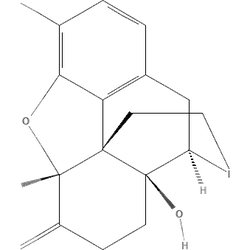
Naloxone Stats & Data
C=CCN1CCC23C4C(=O)CCC2(C1CC5=C3C(=C(C=C5)O)O4)OUZHSEJADLWPNLE-GRGSLBFTSA-NPharmacology
DrugBankDescription
Naloxone is an opioid antagonist medication used to block or reverse the effects of opioid drugs, particularly within the setting of drug overdoses which are rapidly becoming a leading cause of death worldwide. More specifically, naloxone has a high affinity for μ-opioid receptors, where it acts as an inverse agonist, causing the rapid removal of any other drugs bound to these receptors. When taken in large quantities, opioid medications such as morphine, hydromorphone, methadone, heroin, or fentanyl are capable of causing life-threatening symptoms such as respiratory depression, reduced heart rate, slurred speech, drowsiness, and constricted pupils. If untreated, this can progress to vomiting, absent pulse and breathing, loss of consciousness, and even death. Naloxone is indicated for the rapid reversal of these symptoms of central nervous system depression in opioid overdose. It's important to note that naloxone only works on opioid receptors within the body, and is therefore not capable of reversing the effects of non-opioid medications such as stimulants like methamphetamine or cocaine, or benzodiazepines like lorazepam or diazepam. Also known as the brand name product Narcan, naloxone is currently available by intramuscular (IM) or subcutaneous (SubQ) injection, nasal spray, or intravenous (IV) infusion.
Mechanism of Action
Naloxone is a competitive inhibitor of the µ-opioid receptor. Naloxone antagonizes the action of opioids, reversing their effects. If a patient has not taken opioids, naloxone does not have a significant effect on patients.
Pharmacodynamics
Naloxone is an opioid receptor antagonist indicated in the reversal of opioid overdoses. Naloxone has a shorter duration of action than opioids and multiple doses may be required. The therapeutic window of naloxone is wide, as it has no effect if a patient has not taken opioids. Patients treated with naloxone may experience opioid withdrawal and a person administering naloxone should be aware that reversal of opioid overdoses may not resolve all the symptoms a patient is experiencing if other drugs are involved.
Metabolism
Naloxone primarily undergoes glucuronidation to form naloxone-3-glucuronide. Naloxone is also N-dealkylated to noroxymorphone or undergoes 6-keto reduction to naloxol.
Absorption
An intranasal dose of naloxone is 42-47% bioavailable. An 8 mg dose of nasal naloxone reaches a Cmax of 12.3-12.8 ng/mL, with a Tmax of 0.25 hours, and an AUC of 16.7-19.0 h\*ng/mL. A 0.4 mg intramuscular dose reaches a Cmax of 0.876-0.910 ng/mL, with a Tmax of 0.25 hours, and an AUC of 1.94-1.95 h\*ng/mL. A 2 mg intravenous dose reaches a Cmax of 26.2 ng/mL with an AUC of 12.8 h\*ng/mL.
Indication
Naloxone nasal sprays are indicated for the emergency treatment of an opioid overdose or suspected opioid overdose. Intramuscular, intravenous, and subcutaneous injections are indicated for complete or partial reversal of opioid depression, diagnosis of known or suspected opioid overdose, and as an adjunct therapy in the treatment of septic shock. Sublingual tablets and films are formulated with buprenorphine for the treatment of opioid dependence. Naloxone is also formulated with pentazocine as an oral tablet for severe pain. Naloxone has been used off-label for the treatment of neuraxial opioid-induced pruritus.
Half-life
The mean half life of naloxone hydrochloride is 1.8-2.7 hours intranasally, 1.4 hours intramuscularly, and 1.2 hours intravenously. In neonates, the mean half life is 3.1 ± 0.5 hours.
Protein Binding
Naloxone is approximately 45% bound to albumin, but there is significant binding to other proteins.
Elimination
After oral or intravenous administration, naloxone is 25-40% eliminated in the urine within 6 hours, 50% in 24 hours, and 60-70% in 72 hours. The metabolites naloxone-3-glucuronide, noroxymorphone, and naloxol are all detected in the urine.
Volume of Distribution
The volume of distribution of naloxone is 200 L. Naloxone distributes into tissues rapidly. It can also cross the placenta and blood-brain barrier.
Measured Affinities
Guide to PHARMACOLOGYMeasured binding and functional data for naloxone, curated by the IUPHAR/BPS Guide to PHARMACOLOGY. Each row cites the paper it came from. Lower concentrations mean tighter binding — a value in the sub-nanomolar range indicates a very potent interaction.
| Target | Action | Measure | Value | Concentration | Species | Source |
|---|---|---|---|---|---|---|
| μ receptor Oprm1 | Antagonist | pKi | 9 | 1 nM | Mouse | PMID 8114680 |
| μ receptor OPRM1 | Antagonist | pKi | 8.9 | 1.26 nM | Human | PMID 9686407 |
| κ receptor Oprk1 | Antagonist | pIC50 | 8.3 | 5.01 nM | Mouse | PMID 8393575 |
| δ receptor Oprd1 | Antagonist | pKi | 7.8 | 15.85 nM | Mouse | PMID 8114680 |
| δ receptor OPRD1 | Antagonist | pKi | 7.2 | 63.1 nM | Human | PMID 9686407 |
| δ receptor Oprd1 | Antagonist | pIC50 | 6.2 | 630.96 nM | Mouse | PMID 8393575 |
| κ receptor OPRK1 | Antagonist | pKi | — | — | Human | — |
| κ receptor Oprk1 | Antagonist | pKi | — | — | Rat | — |
Reading this. pKi, pEC50 and pIC50 are negative log molar values, so a higher number means a tighter interaction; the concentration column converts them for you. Values from non-human species are laboratory measurements and do not translate directly to human effect. Receptor affinity is not a dose — it describes what a molecule binds, not how much of it is safe to take.
Receptor data from the IUPHAR/BPS Guide to PHARMACOLOGY (v2026.2), licensed CC BY-SA 4.0. Matched to this substance by InChIKey.
Toxicity
DrugBankNaloxone is among the safest drugs in emergency medicine. It has no abuse potential and no effect in a person without opioids in their system, so giving it 'unnecessarily' causes no harm — when in doubt, give it. In opioid-dependent people it precipitates acute withdrawal (the Narcan label lists body aches, diarrhea, tachycardia, fever, runny nose, sweating, yawning, nausea or vomiting, restlessness, shivering, abdominal cramps, weakness, and increased blood pressure): intensely unpleasant, but temporary and very rarely dangerous. The rare serious complication reported after overdose reversal is non-cardiogenic pulmonary edema (roughly 0.2–3.6% of reversals reaching an emergency department, linked to catecholamine surge and to total doses above about 4.4 mg) — a reason titrated dosing beats stacking sprays, never a reason to hesitate. Expired naloxone retains most of its potency for years (kits up to 30 years old still assayed above 90% of label strength), and toxicologists endorse using expired naloxone over none. It is used in pregnancy when the mother's life is at risk.
Toxicity (DrugBank)
If a patient has not taken opioids, naloxone does not have a significant effect on patients. The oral LD50 in mice and rats is >1 g/kg. The intraperitoneal LD50 is 80 mg/kg in mice and 239 mg/kg in rats. The subcutaneous LD50 is 286 mg/kg in mice and 500 mg/kg in rats.