
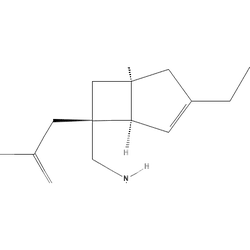
Mirogabalin Stats & Data
FTBQORVNHOIASH-CKYFFXLPSA-NPharmacology
DrugBankDescription
Mirogabalin has been used in trials studying the treatment of Post-herpetic Neuralgia, Pain Associated With Fibromyalgia, and Diabetic peripheral neuropathic pain.
Tolerance & Pharmacokinetics
drugs.wikiNo tolerance chart. Our decay curves for these drugs were estimates, and a curve can make tolerance look longer-lasting than it is, which is the dangerous direction.
How fast tolerance to these drugs fades after a break has not been measured well enough to draw, so don't count on a dose you used to take still being safe: after time off, start with a much smaller amount and don't use alone. Mixing sedatives with each other, with alcohol or with opioids sharply raises the risk of a fatal overdose. If you've been using regularly, don't stop suddenly: withdrawal from benzodiazepines, alcohol or GHB/GBL can cause seizures or delirium, so get medical help to cut down gradually.
Sources: FRANK: benzodiazepines · Alcohol and Drug Foundation: GHB · FDA 2020: benzodiazepine boxed warning · FDA 2019: gabapentinoids and breathing · NHS: alcohol use disorder
Cross-Tolerances
Harm Reduction
drugs.wikiMirogabalin is an α2δ subunit modulator of voltage‑gated calcium channels, not a GABA(A) agonist; expect sedative and ataxic effects from reduced excitatory neurotransmission rather than direct GABAergic action. Combining with opioids or other CNS depressants substantially increases overdose risk due to additive respiratory depression; this pattern has been implicated in European mortality monitoring for gabapentinoids as a class. If an opioid is present during an overdose, naloxone reverses the opioid but not mirogabalin—continued monitoring and supportive breathing are still required. Like other gabapentinoids, abrupt discontinuation after sustained use can precipitate withdrawal (anxiety, insomnia, tremor, nausea; rarely seizures); taper gradually under medical supervision. Dose accumulation occurs in renal impairment—start lower and extend intervals; older adults are more susceptible to dizziness, confusion, and falls. Avoid driving or hazardous tasks for at least 6–8 hours after dosing (longer with higher doses or combinations). Peripheral edema and weight gain can occur in this class; monitor if you have cardiovascular or edema‑prone conditions. To reduce harm: use single‑substance sessions, avoid redosing loops, keep hydrated but not excessive, and never mix with alcohol/benzos/“Z‑drugs”. If using around opioids, ensure ready access to naloxone and do not use alone. Store securely to prevent diversion.
References
Cited references
- DrugBank: Mirogabalin (mechanism, classification, ATC)
- EMCDDA/EUDA DRD meeting report noting gabapentinoids in poisonings and polydrug depressant patterns (pregabalin/gabapentin)
- European Drug Report 2025 (context: depressant polydrug harms and benzodiazepines/opioids)
- EU best‑practice: naloxone reverses opioid component only; continued monitoring required
- DrugWise overview: UK concerns on gabapentinoids with other depressants (respiratory failure/death)