
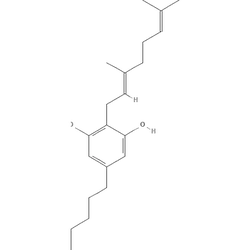
CBG Stats & Data
QXACEHWTBCFNSA-SFQUDFHCSA-NMeasured Affinities
Guide to PHARMACOLOGYMeasured binding and functional data for cannabigerol, curated by the IUPHAR/BPS Guide to PHARMACOLOGY. Each row cites the paper it came from. Lower concentrations mean tighter binding — a value in the sub-nanomolar range indicates a very potent interaction.
| Target | Action | Measure | Value | Concentration | Species | Source |
|---|---|---|---|---|---|---|
| TRPM8 Trpm8 | Antagonist | pIC50 | 6.8 | 158.49 nM | Rat | PMID 38408345 |
| TRPA1 Trpa1 | Agonist | pEC50 | 6.15 | 707.95 nM | Rat | PMID 38408345 |
| Nav1.7 SCN9A | Channel blocker | pIC50 | 5.34 | 4,571 nM | Human | PMID 35297036 |
| Nav1.8 SCN10A | Channel blocker | pIC50 | 5.3 | 5,012 nM | Human | PMID 39835903 |
| Nav1.7 SCN9A | Channel blocker | pIC50 | 4.73 | 18,621 nM | Human | PMID 35297036 |
| TRPM8 Trpm8 | Antagonist | - | — | — | Rat | PMID 21902175 |
Reading this. pKi, pEC50 and pIC50 are negative log molar values, so a higher number means a tighter interaction; the concentration column converts them for you. Values from non-human species are laboratory measurements and do not translate directly to human effect. Receptor affinity is not a dose — it describes what a molecule binds, not how much of it is safe to take.
Receptor data from the IUPHAR/BPS Guide to PHARMACOLOGY (v2026.2), licensed CC BY-SA 4.0. Matched to this substance by InChIKey.
Tolerance & Pharmacokinetics
drugs.wikiTolerance Decay
Acute tolerance: develops within a single session — the reset numbers above apply after sustained heavy use, not after one binge. Within-session tachyphylaxis usually resets largely overnight.
Estimates extrapolated from general cannabinoid use patterns and user reports; formal human CBG tolerance data are lacking.
Cross-Tolerances
Harm Reduction
drugs.wiki• CBG appears non-intoxicating and clear-headed for most users, but human clinical evidence remains limited; treat it as an experimental supplement rather than a proven therapy.
• Quality control varies widely across hemp-derived products; insist on a recent third-party COA reporting potency (CBG/THC), residual solvents, pesticides, heavy metals, and microbial contaminants. Mislabeling and contamination have been repeatedly documented in cannabinoid products.
• To avoid unintended intoxication or drug testing issues, verify Δ9-THC is below legal thresholds in the final product (not just the source hemp) and be mindful that even trace THC can accumulate with frequent dosing.
• Like other lipophilic cannabinoids, oral exposure can be increased by high-fat meals. If you change meal fat content, re-titrate from a lower dose to avoid overshooting effects.
• Cannabinoids can cause transient postural hypotension and dry mouth/eyes; sit or lie down if lightheaded. Those on antihypertensives or α2-agonists (e.g., clonidine; brimonidine eye drops) should start at the low end and monitor blood pressure.
• Avoid driving or operating machinery until you know your response—drowsiness can occur at higher doses or with CNS depressants.
• Inhalation: avoid oils and thickeners (e.g., vitamin E acetate) and unknown diluents; use tested distillates only, at modest temperatures, to reduce thermal degradation products.
• Pregnancy/breastfeeding: cannabinoid exposure in pregnancy is associated with risks with THC-containing products; there are insufficient data for CBG. Best practice is to avoid unless medically justified.
• Pilot and preclinical data suggest potential anxiolytic and anti-inflammatory actions, but CBG is not a substitute for indicated treatments in serious conditions. Discuss with a clinician if using alongside prescription medicines.
• Human pharmacokinetics are not well established; expect interindividual variability and adjust intervals/doses conservatively.
References
Cited references
- DrugBank: Cannabigerol (DB14734) — identification and properties
- Deiana et al., 2012 — PK of CBD, CBDV, THCV, and CBG in rodents (oral and IP)
- NCBI Bookshelf: Marijuana and Glaucoma — cannabinoids reduce IOP for ~3–4 h
- NCBI Bookshelf: Cannabidiol — increased oral exposure with high-fat meals; CYP3A4/2C19 metabolism; drowsiness
- StatPearls: Cannabinoid Antiemetic Therapy — cannabidiol may cause drowsiness; CYP3A4 inhibition note
- NCBI Bookshelf: Cannabidiol — science/marketing/regulatory; frequent mislabeling and contamination of cannabinoid products
- Hi-Ground booklet — EVALI linked to vitamin E acetate in illicit cartridges; avoid lipid thickeners
- NCBI Bookshelf: The Health Effects of Cannabis and Cannabinoids — prenatal/perinatal exposure risks (THC data)
- DrugBank target/mechanistic references for cannabinoids acting at TRP channels
- Wikipedia – Cannabigerol (general overview)
- Cascio MG et al. (2010) — CBG as α2-adrenoceptor agonist and 5-HT1A antagonist (preclinical)
- Brierley DI et al. (2016) — Neuroprotective signals of CBG (preclinical)